
Key Takeaways
- Medical record retrieval follows a defined, multi-stage process. Successful retrieval depends on accurate provider routing, complete authorization, timeline management, consistent follow-up, fee resolution, and properly documented delivery.
- Many delays are preventable at the beginning. Requests often stall because they go to the wrong department, use outdated provider information, or include incomplete authorization forms.
- Authorization quality directly affects turnaround time. Missing signatures, dates, expiration information, record date ranges, or required HIPAA elements can cause providers to reject a request and restart the process.
- Provider type significantly affects retrieval timelines. Private practices may respond relatively quickly, while hospitals, integrated health systems, behavioral health providers, and other complex facilities may take substantially longer.
- Active follow-up is essential. Track requests through documented follow-ups, fee resolution, and escalation rather than submitting them and leaving them with the provider.
- Delivery should be verified, not just received. For legal and insurance matters, teams should confirm that the record set is complete, properly certified when required, delivered securely, and supported by a documented chain of custody.
- Managed retrieval can reduce the administrative burden of high-volume requests. Outsourcing provider outreach, follow-up, fee management, escalation, and delivery can give law firms and other organizations a more standardized and visible retrieval workflow.
The medical record retrieval process is far more complex than most people expect. Many assume it works like this: send a signed authorization, wait a few days, and receive the records.
In practice, a request that looks simple on the surface can stall for weeks when a single field is missing from an authorization form or when it gets routed to the wrong department inside a 500-bed hospital system.
Law firms, insurance claims teams, and veterans’ advocates who depend on medical records to move cases forward understand this frustration well.
The good news is that medical record retrieval isn’t random. It has defined stages, predictable failure points, and a clear benchmark that separates well-managed retrieval from the rest.
This article walks through every stage of the workflow, from initial provider outreach to certified delivery, and explains where delays enter and how to prevent them.
Provider outreach and request routing: getting the medical record retrieval process started right
The first step in obtaining medical records is not filling out a form. It is confirming exactly where that form needs to go.
For hospitals, the correct destination is the Health Information Management (HIM) or Release of Information (ROI) department, not the front desk or the treating physician’s office.
For private practices, a quick phone call to confirm the office’s preferred submission method saves days of confusion. Imaging centers add another layer: requesters often need to specify whether they want the radiology report, the actual images, or both, and those may be handled by entirely separate staff.
Misrouting is one of the most common and most preventable early-stage errors. A request sent to the wrong department or physical location within a multi-campus health system can sit unprocessed for days before anyone notices it at all.
How provider type changes the outreach approach
Hospitals route everything through their formal ROI queue, so checking the patient portal first can save the submission entirely. Private practices are faster to reach but vary widely in submission preferences: some accept faxes, others prefer secure email, and a few still require mail. Imaging centers typically accept requests by fax or their own portal, but confirming the report-versus-images distinction upfront prevents a second round of outreach later.
Building an accurate provider contact database
Providers change fax numbers, merge practices, and redirect records departments more often than most requesters realize. An outdated contact does not just slow a single request; it means starting over after the submission has already been sent. Teams handling high-volume retrieval benefit significantly from maintaining a verified, current routing database as a living resource. Full-service retrieval partners treat this as standard infrastructure, which is one reason their submissions move faster than manual in-house efforts.
Building an authorization packet that actually gets accepted
A HIPAA-compliant authorization is not just a signature on a generic release form. It is a specific document with federally required elements, and missing even one of them gives the provider legal grounds to reject the request outright. This is one of the top causes of retrieval delays, and it is entirely preventable.
A valid authorization packet must include all of the following:
- The patient’s full name and date of birth
- The custodian of records’ name and address
- A specific description of the records requested, including date ranges
- The recipient’s name and delivery details
- The purpose of the disclosure
- An expiration date or expiration event
- The patient’s or authorized representative’s signature and date
- All three required HIPAA notices: the right to revoke, the conditioning statement, and the redisclosure risk warning
The HIPAA elements that most forms get wrong
The most commonly missed fields are vague or absent date ranges, missing expiration dates, and unsigned or undated forms. A request for “all records” without a defined date range forces the provider to seek clarification before processing begins, which restarts the clock. Standardizing an intake checklist that verifies every required field before submission eliminates this category of delay almost entirely.
Sensitive record categories that require additional authorization
Behavioral health records, substance use disorder records, HIV-related records, and records involving minors follow stricter rules than standard HIPAA authorizations. Each category may require a supplemental authorization form, and submitting a standard release for these record types results in rejection. Identifying sensitive categories at intake, before submission, prevents a second round of outreach and the additional days that come with it.
Medical record retrieval process turnaround times by provider type
Understanding what to actually expect, rather than what the law permits, is essential for managing case timelines.
Small private practices commonly respond in 7 to 14 days. Specialty clinics run 14 to 30 days. Hospital systems average 30 to 60 days, and large integrated health systems can stretch to 60 to 90 days or more. Behavioral health and substance use disorder records routinely take 45 to 90 days because of the additional authorization requirements covered above.
HIPAA gives providers up to 30 days to respond with one allowable 30-day extension, making the legal maximum 60 days under federal rules. Many providers treat that legal window as a default rather than a deadline to beat, a habit that accounts for much of the routine delay teams experience.
Why hospital systems take so much longer than private practices
Hospital systems operate with formal ROI queue processes, multi-step approval chains, and often paper-based workflows inside legacy records systems.
A single HIM department may be processing thousands of requests simultaneously. Contrast that with a small private practice where one office manager handles records requests directly and can pull a chart the same afternoon.
The structural difference explains the gap in records retrieval turnaround time and sets the context for why active follow-up matters so much at this provider tier.
The factors that compress or extend the timeline
Authorization quality is one of the biggest controllable variables in the medical record retrieval process. Incomplete authorizations commonly restart the clock; a defective submission moves no faster than the time it takes the provider to reject it and wait for a corrected version. Clean requests consistently move faster than defective ones, regardless of provider type.
Beyond authorization quality, electronic submission is consistently faster than mailed paper. Resolving fee questions before submission eliminates one common hold point. And active follow-up on every open request is the factor that separates a faster turnaround from a months-long delay. An unmonitored request almost always takes longer than a tracked one.
The follow-up stage: where most retrievals quietly stall
Follow-up is the most underestimated stage of the medical record retrieval process. Once a request is submitted, it does not manage itself.
Providers with high request volume can let a submission sit for days or weeks, without anyone noticing, especially if no one is actively checking its status.
An effective follow-up cadence looks like this: check in around day 10 for small providers, day 14 for hospital systems, and escalate to a supervisor or ROI department lead if no response is received within a defined window. Document every contact attempt with a date, name, and outcome.
Managing provider fees that hold records up
Some providers require payment before releasing records, and fee structures vary significantly by state. Per-page rates, search fees, certification fees, and off-site storage retrieval charges all appear across U.S. providers.
Unresolved fees are one of the most common reasons a completed request never reaches delivery. Confirming fee policies before submission and authorizing payment as part of the intake process removes this barrier entirely.
When and how to escalate a stalled request
Escalation follows a clear sequence: initial follow-up call, written follow-up by email or fax, escalation to the ROI supervisor, and, if applicable, a written notice citing the state’s required response deadline. The tone should remain professional throughout.
The goal is to move the request forward, not to create friction with a provider you will work with again on the next case. Documented escalation also creates a record that supports any subsequent dispute about delay.
Certified delivery and closing the chain of custody
At the final stage of the process, records are delivered, but the format and documentation of that delivery matter as much as the content.
For legal and insurance use, certified records carry a custodian’s attestation that the copy is a true and accurate reproduction of the original. Uncertified records are appropriate for internal review but may not meet admissibility requirements in court or regulatory standards for formal proceedings.
An auditable chain of custody is not optional for evidentiary use. Every handoff, from provider to retrieval service to end recipient, should be documented with timestamps and delivery confirmation. A gap in that chain creates an authentication problem at the worst possible moment.
What makes a medical record court-ready
Court-ready records require custodian certification, documentation of the delivery method, and a complete record set.
Missing imaging, missing treatment notes, or a record that covers only part of the requested date range can undermine a case even when the records themselves are authentic.
Verification at delivery matters as much as verification at intake, and a delivery that arrives missing key components should be flagged immediately rather than filed and discovered later.
Common errors at the delivery stage
The errors that create downstream problems include the wrong delivery format when digital was specified, a missing certification stamp on records intended for court, delivery to the wrong party, and records delivered without a clear confirmation log. Each of these is catchable before it affects a case or claim, but only if someone is actively reviewing the delivery rather than simply marking the request closed.
Handling retrieval in-house vs. using a full-service managed model
In-house retrieval costs more than the time spent on individual requests. Staff handling records manually juggle provider outreach, form preparation, follow-up calls, fee approvals, and delivery tracking simultaneously across potentially dozens of open files. Every stalled request requires someone to notice it, chase it, and document the resolution. For high-volume practices or insurance teams, this operational burden compounds directly with caseload.
A full-service retrieval model transfers the entire workflow to a dedicated partner who manages every stage: provider outreach, authorization submission, active follow-up, fee handling, escalation, and certified delivery. The difference is not just convenience. It is consistency and speed at scale, delivered the same way across every request. For teams managing complex or high-volume medical records requests, that consistency translates directly into predictable case timelines.
What a managed retrieval workflow looks like in practice
Record Retrieval Solutions (RRS) handles every stage of the medical record retrieval process end-to-end, from provider outreach and authorization submission through fee management and persistent follow-up until records are complete and delivered.
Our proprietary platform, RecordSync,io, centralizes every request, follow-up, escalation, and delivery in a single HIPAA-compliant portal, giving clients real-time visibility without the administrative overhead of tracking requests manually.
RRS reports a 15-day average turnaround across its managed workflows, reflecting the operational discipline that dedicated retrieval infrastructure enables.
Who benefits most from outsourcing retrieval?
Personal injury and mass tort law firms managing high-volume caseloads see the most immediate impact, because the efficiency gap between in-house and outsourced retrieval widens directly with the number of requests in flight.
Insurance claims teams operating under strict claim timelines benefit from the predictability a managed model provides. Solo practitioners and boutique firms without dedicated staff gain a reliable partner that handles the complexity of provider outreach, follow-up, and certified delivery without disrupting core workflow. The value scales with volume, but the operational relief starts from the first request.
The takeaway for every team that handles record retrieval
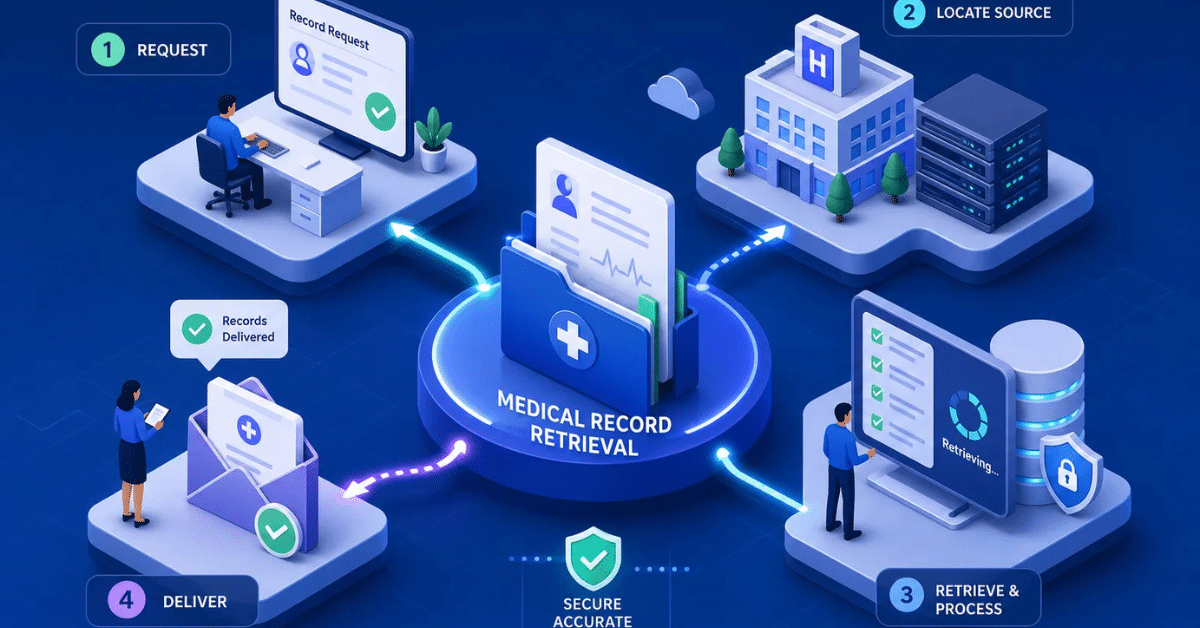
The medical record retrieval process has five defined stages: provider outreach and routing, authorization submission, timeline management, active follow-up and fee resolution, and certified delivery. Each stage has predictable failure points, and most of them are preventable with the right preparation and process.
If medical record retrieval is taking longer than it should, the issue lives in one of these stages. Knowing which one is the first step to fixing it.
For teams that want a structured medical record retrieval process without the overhead of building it from scratch, a full-service partner like Record Retrieval Solutions (RRS) manages every stage end to end, with RecordSync providing visibility to confirm progress at every step.
Contact the RRS team directly to see what a managed medical record retrieval process looks like for your case type and volume.
FAQs
What are the main stages of the medical record retrieval process?
The process runs from initial provider outreach and request routing through authorization validation, record retrieval (including any imaging-specific steps), and certified delivery. Each stage has predictable failure points, such as misrouting, incomplete authorizations, or outdated contact information, which determine whether a request moves quickly or stalls.
Why do medical record requests often take weeks to process?
Requests often stall because they are sent to the wrong department or physical location, an authorization is missing required HIPAA elements, or the requester used an outdated provider contact. A single missing field or misroute can leave a request unprocessed for days or weeks.
What must a HIPAA-compliant authorization packet include?
A valid authorization packet must include the patient’s full name and date of birth, the custodian of records’ name and address, a specific description of the records requested (including date ranges), the recipient’s name and delivery details, the purpose of the disclosure, an expiration date or expiration event, the patient’s or authorized representative’s signature and date, and all three required HIPAA notices: the right to revoke, the conditioning statement, and the redisclosure risk warning.
How can I prevent delays when requesting medical records?
Confirm the exact destination and submission method before sending anything, maintain a verified, current provider routing database, and assemble a complete HIPAA-compliant authorization packet. Teams handling high-volume retrieval often use full-service retrieval partners or living contact databases to move submissions faster than manual in-house efforts.





